Vasculearn Network · Clinical Hub
Venous Thromboembolism (VTE)
Printed November 14, 2026 · vln.org/hcp/disease-state/vte
Clinical Overview
A swollen leg or sudden breathlessness may be the first sign of a clot, and the start of months of uncertainty for the patient. VTE care connects urgent diagnosis with a longer conversation about recurrence, bleeding, and returning to everyday life.
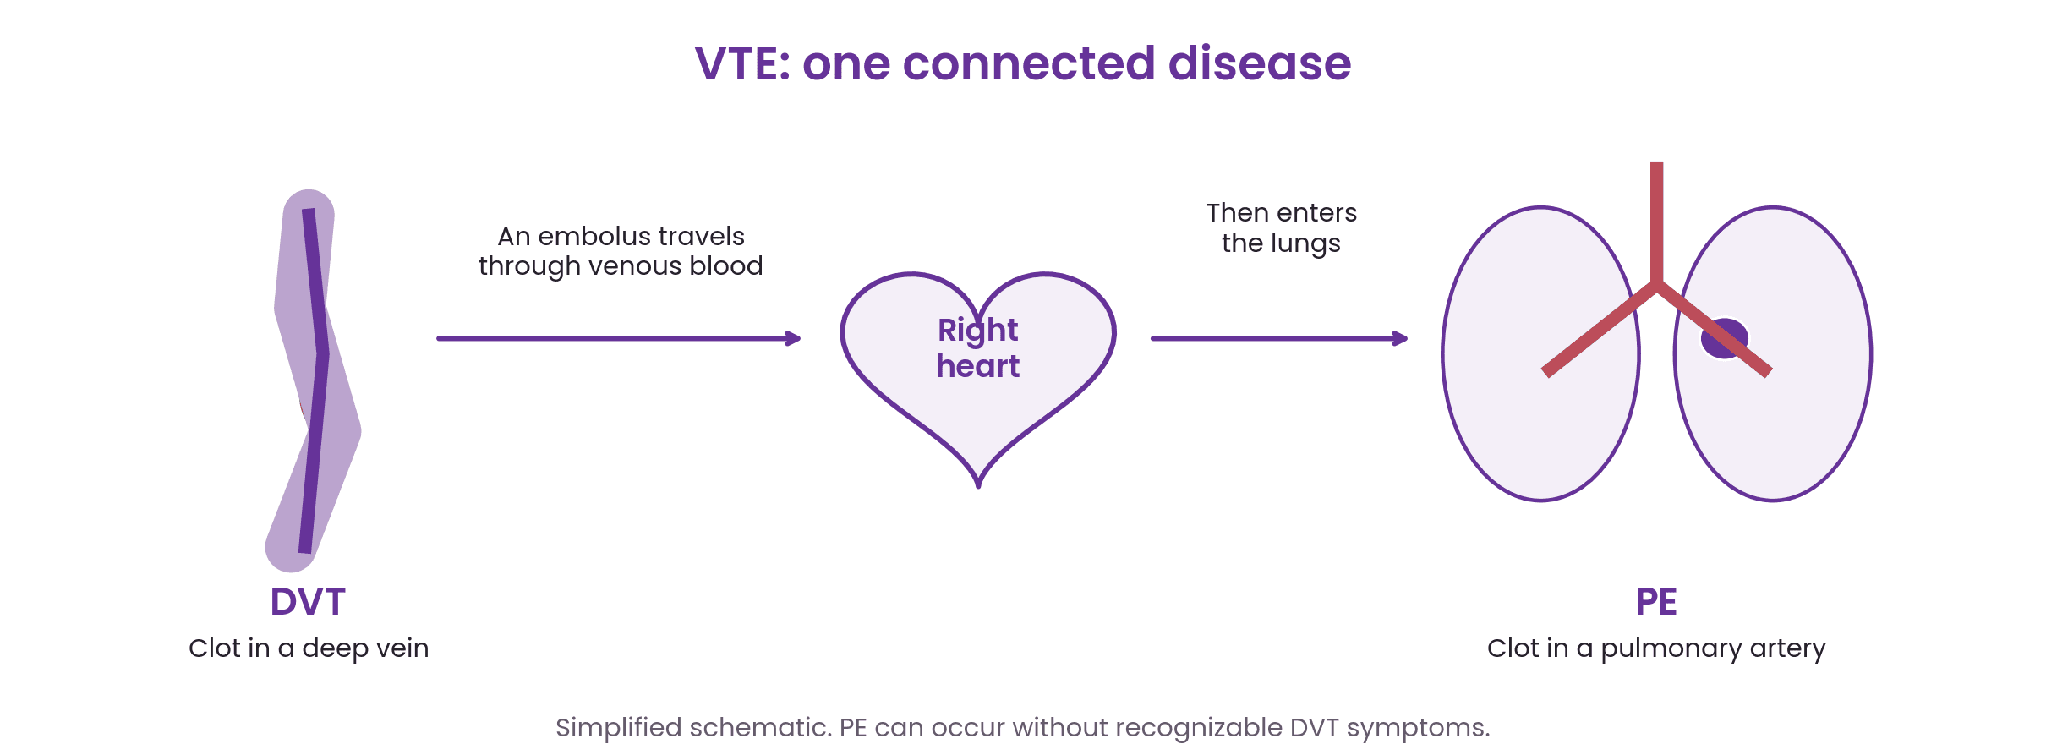
VTE includes deep vein thrombosis (DVT) and pulmonary embolism (PE). DVT usually develops in the legs or pelvis, but can involve the arms. A clot that travels to the pulmonary arteries can impair oxygenation and strain the right heart; PE may occur without recognizable leg symptoms.
- Confirm the diagnosis: Symptoms alone cannot establish or exclude VTE. Combine clinical probability with appropriate testing.
- Treat the immediate risk: Anticoagulation prevents extension and recurrence while the body clears the clot. Hemodynamic instability or a threatened limb changes the urgency and treatment pathway.
- Look beyond the clot: The trigger, bleeding risk, medication access, and patient priorities shape treatment duration and recovery.
Diagnosis
Start with probability, then choose the test
The ASH VTE Diagnosis Guideline supports structured pathways rather than D-dimer or imaging in isolation. The Wells DVT score and Wells PE score help estimate pretest probability; neither confirms VTE.
Presentation | Diagnostic approach |
|---|---|
Suspected DVT | Unilateral swelling, pain, warmth, or discoloration warrants assessment. In a validated low-probability pathway, a negative high-sensitivity D-dimer can exclude DVT; otherwise use compression ultrasonography. |
Negative proximal ultrasound | If clinical probability remains significant, follow the pathway for repeat proximal ultrasound, commonly at about 1 week, or whole-leg imaging. Consider pelvic/iliac imaging when symptoms suggest proximal obstruction. |
Suspected PE | Assess new dyspnea, pleuritic pain, tachycardia, hypoxemia, hemoptysis, or syncope. Use D-dimer for appropriate low/intermediate-probability presentations; proceed directly to imaging when probability is high. |
PE imaging | CT pulmonary angiography is usual first-line imaging. V/Q scanning is an alternative when contrast or other patient factors favor it. A nondiagnostic study requires further assessment, not reassurance. |
Use rule-out tools within their intended setting
- PERC rule: In carefully selected adults with very low clinical suspicion for PE, all-negative criteria may avoid D-dimer testing. Do not apply it to higher-risk presentations or assume validity in pregnancy.
- D-dimer: A positive result is nonspecific and does not diagnose VTE. Age-adjusted thresholds can improve specificity in adults over 50 within validated pathways; confirm the assay units and local cutoff.
- Unstable patients: Activate emergency assessment and the PE response pathway. Bedside echocardiography can inform urgent decisions when transport for CT is unsafe; it does not routinely exclude PE.
For possible recurrent DVT, compare with prior imaging to distinguish new thrombosis from residual changes. Pregnancy, unusual clot sites, or discordant tests warrant an adapted diagnostic pathway and specialist input.
Describe the event and its context
Subtype or context | Why it matters |
|---|---|
Proximal leg DVT | Popliteal vein or above: higher embolic risk; anticoagulation is generally indicated. |
Isolated distal DVT | Calf veins: extension risk, symptom burden, bleeding risk, and reliable serial imaging determine treatment versus surveillance. |
Upper-extremity DVT | Often catheter-associated; assess device need, cancer, and venous obstruction. Effort thrombosis may require vascular evaluation. |
PE | Severity reflects cardiopulmonary impact, not clot size or a “saddle” label alone. |
Temporary versus ongoing risk | Document surgery, hospitalization/immobility, trauma, hormones, pregnancy, active cancer, or another persistent factor. An event without an identifiable trigger is often termed unprovoked. |
Assess PE severity and disposition
The 2026 Multisociety Acute PE Guideline introduces clinical categories A–E. Use the complete framework, including hemodynamics, respiratory status, clinical severity, biomarkers, and right-ventricular assessment.
Category | Broad clinical profile |
|---|---|
A | Asymptomatic PE. |
B | Symptomatic PE with low clinical severity. |
C | Symptomatic PE with elevated clinical severity, including relevant biomarker or right-ventricular abnormalities. |
D | Incipient cardiopulmonary failure. |
E | Cardiopulmonary failure with persistent hypotension. |
Selected stable patients may be treated at home. Hestia criteria or the Pulmonary Embolism Severity Index (PESI) support assessment, but also confirm medication access, home support, bleeding risk, and prompt follow-up. Categories C–E generally require hospitalization.
Order thrombophilia tests selectively
Use the ASH Thrombophilia Testing Guideline when a result could change duration, drug choice, or family counseling. Routine panels are rarely helpful; selected hormonal or nonsurgical transient-risk events may merit testing. Coordinate timing because acute thrombosis and anticoagulants can affect results.Treatment
Choose an anticoagulant the patient can sustain
The ASH VTE Treatment Guideline and 2024 CHEST VTE Compendium support DOAC treatment for many eligible patients. Select by renal/hepatic function, interactions, bleeding risk, pregnancy, antiphospholipid syndrome (APS), cost, and dosing preference.
Option | Practical considerations |
|---|---|
Apixaban | Oral treatment without a heparin lead-in: 10 mg twice daily for 7 days, then 5 mg twice daily. Twice-daily adherence matters. |
Rivaroxaban | Oral treatment without a heparin lead-in: 15 mg twice daily for 21 days, then 20 mg daily. The 15- and 20-mg doses require food. |
Dabigatran or edoxaban | Require at least 5 days of therapeutic parenteral anticoagulation before starting oral treatment; check agent-specific renal and other dosing requirements. |
LMWH / UFH | Parenteral options when clinically indicated. LMWH is recommended over UFH for most patients with PE needing initial parenteral treatment; selected situations require an individualized approach. |
Warfarin | Remains important for selected APS patients and when affordability or other factors favor it. Overlap with therapeutic parenteral anticoagulation for at least 5 days and until the INR is therapeutic; usual target 2–3. |
In the 2026 COBRRA trial, apixaban caused less clinically relevant bleeding than rivaroxaban during 3 months of acute VTE treatment. This supports apixaban when bleeding risk is a priority, while other agents may better fit access, adherence, or clinical circumstances.
These are common adult regimens, not a substitute for agent-specific prescribing information. VTE treatment doses differ from AF dose-reduction rules. Check CBC, renal/hepatic function, pregnancy status when relevant, and interacting drugs before prescribing.
Escalate when the clot threatens circulation
- PE reperfusion: Systemic thrombolysis, catheter-based treatment, or surgery may be appropriate for cardiopulmonary failure or selected patients deteriorating toward it. Use the PE response team to weigh trajectory, bleeding risk, expertise, and transfer needs; RV strain alone does not mandate intervention.
- DVT intervention: The ESVS Venous Thrombosis Guideline supports urgent specialist assessment for limb-threatening thrombosis and selected severe iliofemoral disease. Most DVT is managed with anticoagulation rather than clot-removal procedures.
Set duration—and a date to reconsider it
For proximal DVT or PE, treat for at least 3 months; the primary treatment phase is generally 3–6 months. Decide about continuing therapy from recurrence risk, bleeding risk, and patient preference rather than whether the clot has disappeared on imaging.
Clinical setting | Duration decision |
|---|---|
First event after a major reversible trigger | When the trigger has resolved, treatment can often stop after about 3 months, following reassessment. |
No clear reversible trigger or persistent risk | Extended treatment is often appropriate when bleeding risk is acceptable. Reassess periodically and after changes in health, medication, or preferences. |
Recurrent VTE | Many patients need indefinite anticoagulation, especially after recurrent unprovoked events. Confirm recurrence and evaluate adherence, interactions, and underlying drivers. |
Extended oral treatment | After at least 6 months, reduced-dose apixaban or rivaroxaban may suit eligible patients. High-recurrence-risk conditions may need a different strategy; aspirin provides less protection and is not equivalent anticoagulation. |
Adapt treatment to the patient
- Active cancer: The ASH Cancer-Associated VTE Guideline supports DOACs or LMWH according to tumor site, GI/GU bleeding risk, interactions, platelet count, and absorption. Continue while risk remains active, with reassessment. The API-CAT trial supports reduced-dose apixaban after ≥6 months in selected patients with active cancer; it is not a universal dose change.
- Pregnancy and lactation: Follow the ASH Pregnancy VTE Guideline. LMWH is the usual treatment during pregnancy; DOACs are avoided in pregnancy and breastfeeding. LMWH and warfarin are options during breastfeeding.
- Selected APS or complex disease: Warfarin is generally favored over DOACs in high-risk APS, especially triple-positive disease. Severe renal/hepatic impairment, unusual sites, or VTE despite treatment warrant specialist-directed care.
- Limited clot burden: Selected low-risk isolated distal DVT may be followed with serial ultrasound over 2 weeks; anticoagulate if extension occurs or risk/symptoms favor treatment. Surveillance for isolated subsegmental PE is a narrow, specialist-guided option requiring exclusion of proximal DVT and reliable follow-up.
Plan procedures and interruptions
Balance procedure bleeding risk, renal function, anticoagulant, and time since VTE; recent VTE increases interruption risk. Specify the last dose, whether bridging is needed, and restart timing. Most DOAC interruptions do not require bridging. Use the VLN Procedure Playbook to help patients follow the coordinated plan. Avoid routine IVC filters; when anticoagulation is contraindicated and a filter is used, document reassessment and retrieval.
Prevention
Build protection into the care already happening
Prevention works best when the plan fits the patient’s life. Use hospital pathways, pharmacy support, primary care, and the existing specialty team to connect prophylaxis, medication access, and recovery—rather than adding another disconnected checklist. Use the VLN VTE Clinician Communication Tool to guide conversations from diagnosis through treatment and follow-up.
- Prevent a first event: The ASH Medical VTE Prevention Guideline supports risk- and bleeding-based prophylaxis for hospitalized medical patients. Surgical and cancer settings need their own pathways; do not extend hospital prophylaxis or prescribe outpatient prophylaxis automatically.
- Anticipate changes: Hospitalization, surgery, reduced mobility, hormones, pregnancy, and cancer treatment can change risk. Revisit prevention during these transitions. Long-distance travel advice should reflect personal risk; routine anticoagulation is not needed for every traveler.
- Make treatment manageable: At existing visits, ask about missed doses, cost, bruising, heavy menstrual bleeding, falls, and new medications. A pharmacist or anticoagulation service can resolve practical barriers; patients should not have to ration or stop treatment on their own.

Follow recovery, not just the prescription
- After DVT: Persistent swelling, heaviness, pain, or skin changes may reflect post-thrombotic syndrome. Encourage appropriate activity; compression can help selected patients’ symptoms but is not routinely prescribed solely to prevent the syndrome.
- After PE: Ask about breathlessness, exercise tolerance, and function at follow-up visits for at least a year. Persistent symptoms after approximately 3 months warrant assessment for other causes and chronic thromboembolic pulmonary disease or pulmonary hypertension, with referral when indicated.
- Restore confidence: Discuss work, travel, intimacy, movement, and fear of another clot. Link VLN patient resources to the follow-up plan. Give clear instructions for urgent assessment of new breathlessness, chest pain, syncope, new unilateral swelling, or significant bleeding.
Health Equity
An effective VTE plan must be affordable, understandable, and reachable. These practical requirements belong in treatment selection and discharge planning.
- Medication access: Confirm the actual out-of-pocket cost and a supply before discharge. Warfarin may cost less but requires dependable INR testing, transport, and dose communication; compare the full burden with DOAC assistance or alternatives.
- Communication and continuity: Use professional interpreters, plain-language instructions, and teach-back. Assign a follow-up contact and explain who manages refills, bleeding concerns, and procedures.
- Support daily life: Consider work schedules, caregiving, housing, disability, travel distance, and menstrual health. Reuse pharmacy, nursing, social work, and community support to address barriers without making the patient coordinate everything.
Acronyms & Glossary
Term | Meaning |
|---|---|
APS | Antiphospholipid syndrome |
CTPA / V/Q | CT pulmonary angiography / ventilation–perfusion scan |
CTEPD / CTEPH | Chronic thromboembolic pulmonary disease / pulmonary hypertension |
DOAC | Direct oral anticoagulant |
DVT / PE / VTE | Deep vein thrombosis / pulmonary embolism / venous thromboembolism |
INR / IVC | International normalized ratio / inferior vena cava |
LMWH / UFH | Low-molecular-weight heparin / unfractionated heparin |
PERC / PESI | Pulmonary Embolism Rule-out Criteria / Pulmonary Embolism Severity Index |
PERT / RV | Pulmonary embolism response team / right ventricle |
PTS | Post-thrombotic syndrome |
Unprovoked VTE | VTE without an identifiable provoking risk factor |